A 2025 Austrian study found perforations in 17.4% of 1,771 surgical gloves (309 gloves) collected during intertrochanteric fracture fixation (Santol et al., 2025). A separate 2025 meta-analysis reported lower odds of inner-glove perforation with double gloving than single gloving: OR 0.20, 95% CI 0.14–0.31 (Singh et al., 2025). The ChEETAh trial found an adjusted surgical-site infection risk ratio of 0.87 when teams changed both gloves and instruments before abdominal wound closure (NIHR Global Research Health Unit on Global Surgery, 2022). This article brings together 31 study-specific data points and four regulatory testing parameters, with sources and context for interpreting each figure. It explains what the numbers measure and where comparisons are valid.
Evidence reviewed: October 20, 2026. Publication years are stated throughout; older findings are labeled as historical evidence.
Key Takeaways
- 17.4% of gloves were perforated (309/1,771) in one Austrian fracture-fixation study; this is not a universal surgical-glove failure rate (Santol et al., 2025).
- Surgeons’ glove perforation was 25.8%, compared with 12.5% for assistants and 12.6% for scrub nurses in that same study (Santol et al., 2025).
- Glove-pair microperforation rose from 15.4% to 23.7% across shorter and longer wear categories in a historical German study (Partecke et al., 2009).
- Matched inner-and-outer perforation had an OR of 0.10 with double gloving versus single-glove perforation; this is not an infection-reduction percentage (Singh et al., 2025).
- Indicator double gloves had a detection OR of 8.64 versus single gloves; detection and physical protection are different outcomes (Singh et al., 2025).
- Combined glove-and-instrument change had an adjusted SSI risk ratio of 0.87 in ChEETAh; gloves alone were not isolated (NIHR Global Research Health Unit on Global Surgery, 2022).
- U.S. acceptance sampling uses AQL 1.5 for surgeons’ gloves and 2.5 for examination gloves; AQL is not an observed defect rate (21 CFR 800.20).
- A 2025 model estimated 22.60 kg CO₂e lower emissions per contaminated-dirty abdominal procedure in LMICs under base-case assumptions; worst-case assumptions reversed the benefit (Ledda et al., 2025).
- 47.59% of operations versus 8.81% of individual gloves showed perforation in one Nepalese orthopedic cohort, demonstrating the importance of denominators (Bhandari et al., 2025).
- Superficial SSI occurred in 7/32 microperforation-positive versus 11/505 intact-glove cesarean cases in a Turkish cohort; this observational comparison does not establish causation (Akbulut et al., 2025).
1. Glove Perforation by Clinical Role and Wear Duration
Perforation depends on the clinical setting and the unit being counted. Role comparisons within one study are more informative than combining unrelated procedures.
The Austrian fracture-fixation study found perforations in 309 of 1,771 used gloves. The prospective series involved 148 procedures; visual and water-fill testing assessed glove damage (Santol et al., 2025).
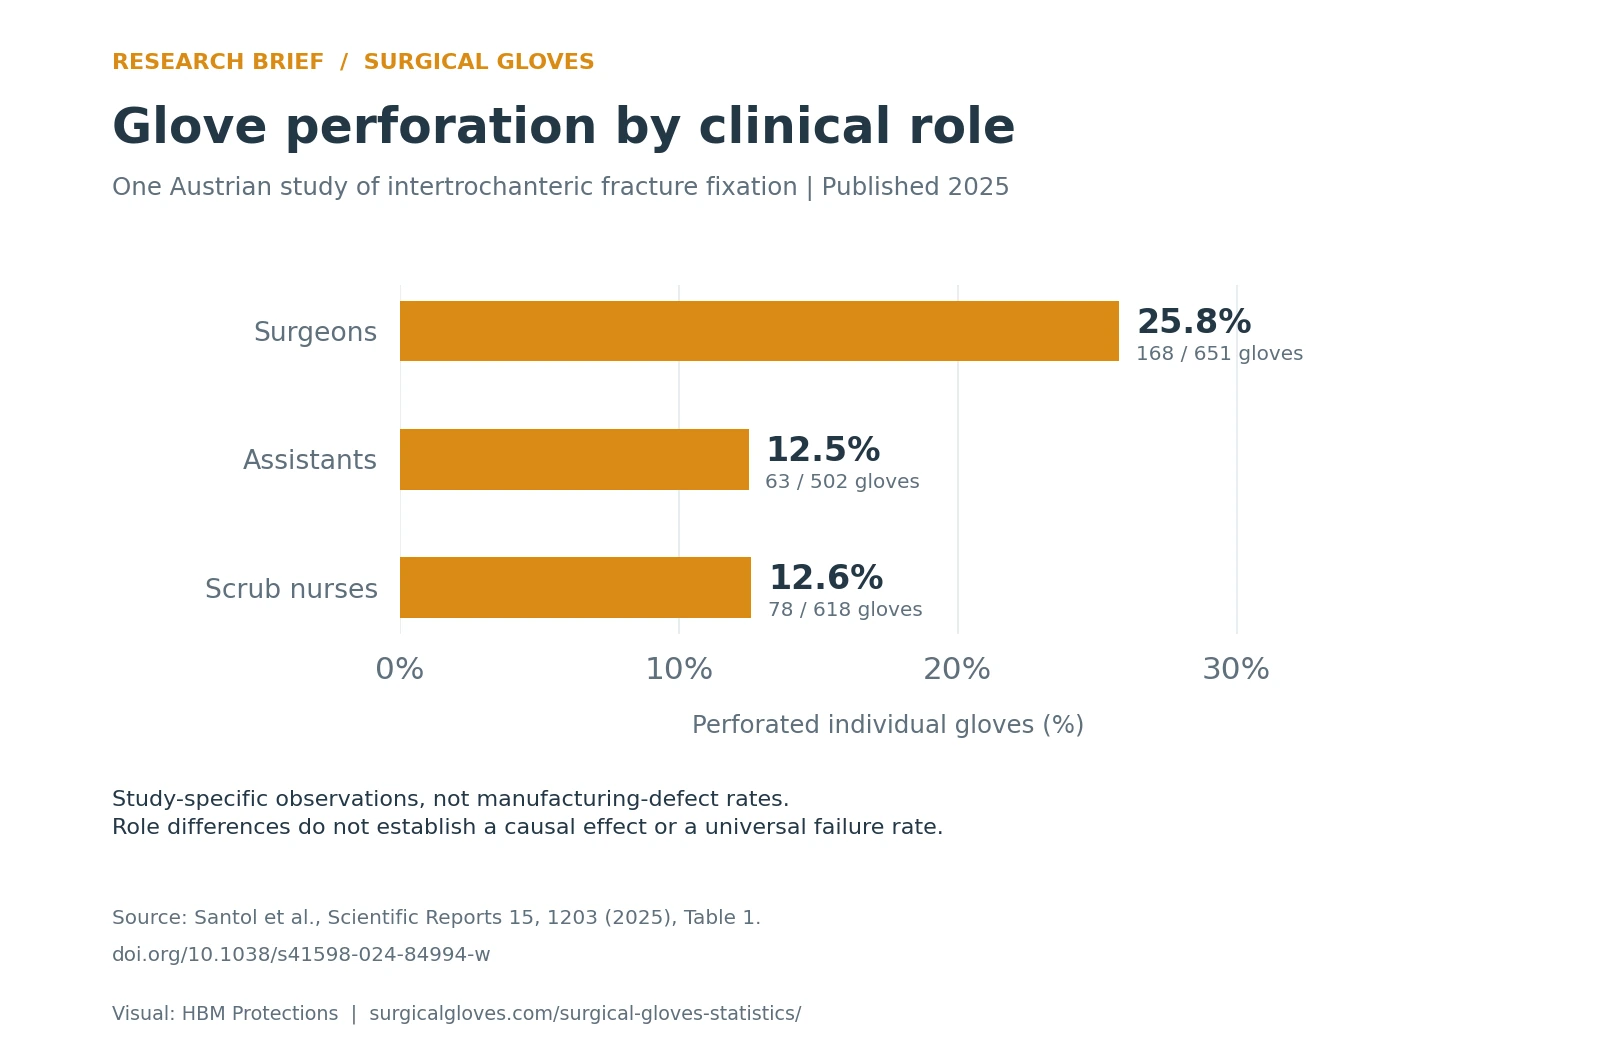
Glove perforation by clinical role in an Austrian fracture-fixation study. Source: Santol et al., 2025. Visual: HBM Protections.
| Metric | Value | Source |
|---|---|---|
| Overall perforated gloves | 17.4% — 309/1,771 gloves | Santol et al., 2025 |
| Surgeons’ perforated gloves | 25.8% — 168/651 | Santol et al., 2025 |
| Assistants’ perforated gloves | 12.5% — 63/502 | Santol et al., 2025 |
| Scrub nurses’ perforated gloves | 12.6% — 78/618 | Santol et al., 2025 |
The Austrian figures count individual gloves used during fracture fixation, not manufacturing defects. Surgery-level percentages with inconsistent denominators in that publication are excluded.
A Nepalese orthopedic study illustrates why the counting unit matters: 47.59% of operations involved a perforated glove, whereas 8.81% of individual gloves were perforated. Its cross-sectional sample covered 166 operations over three months, with both surgeons wearing inner and outer gloves (Bhandari et al., 2025).
| Metric | Value | Source |
|---|---|---|
| Operations with a perforated glove | 47.59% — 79/166 | Bhandari et al., 2025 |
| Overall glove perforation | 8.81% — 117/1,328 gloves | Bhandari et al., 2025 |
| Trauma operations with a perforated glove | 50.45% — 56/111 | Bhandari et al., 2025 |
The two percentages describe the same cohort, not conflicting estimates. The study examined 1,328 individual gloves, including inner and outer layers. Its operation-level and glove-level percentages use different denominators.
A German prospective study selected 139 visually intact scrub-nurse glove pairs collected in June–August 2023. Water testing subsequently revealed concealed damage (Euler-Schmidt et al., 2025).
| Metric | Value | Source |
|---|---|---|
| General-surgery scrub-nurse pairs with concealed perforation | 25% — 14/57 | Euler-Schmidt et al., 2025 |
| Trauma-surgery scrub-nurse pairs with concealed perforation | 28% — 23/82 | Euler-Schmidt et al., 2025 |
The department difference was not statistically significant. Glove changes and long-duration outliers were excluded; only outer gloves were collected when double gloving. These selected-pair results cannot be compared directly with unselected glove samples.
A historical German prospective study examined 898 glove pairs collected over nine months. Either glove having a microperforation made the pair positive (Partecke et al., 2009).
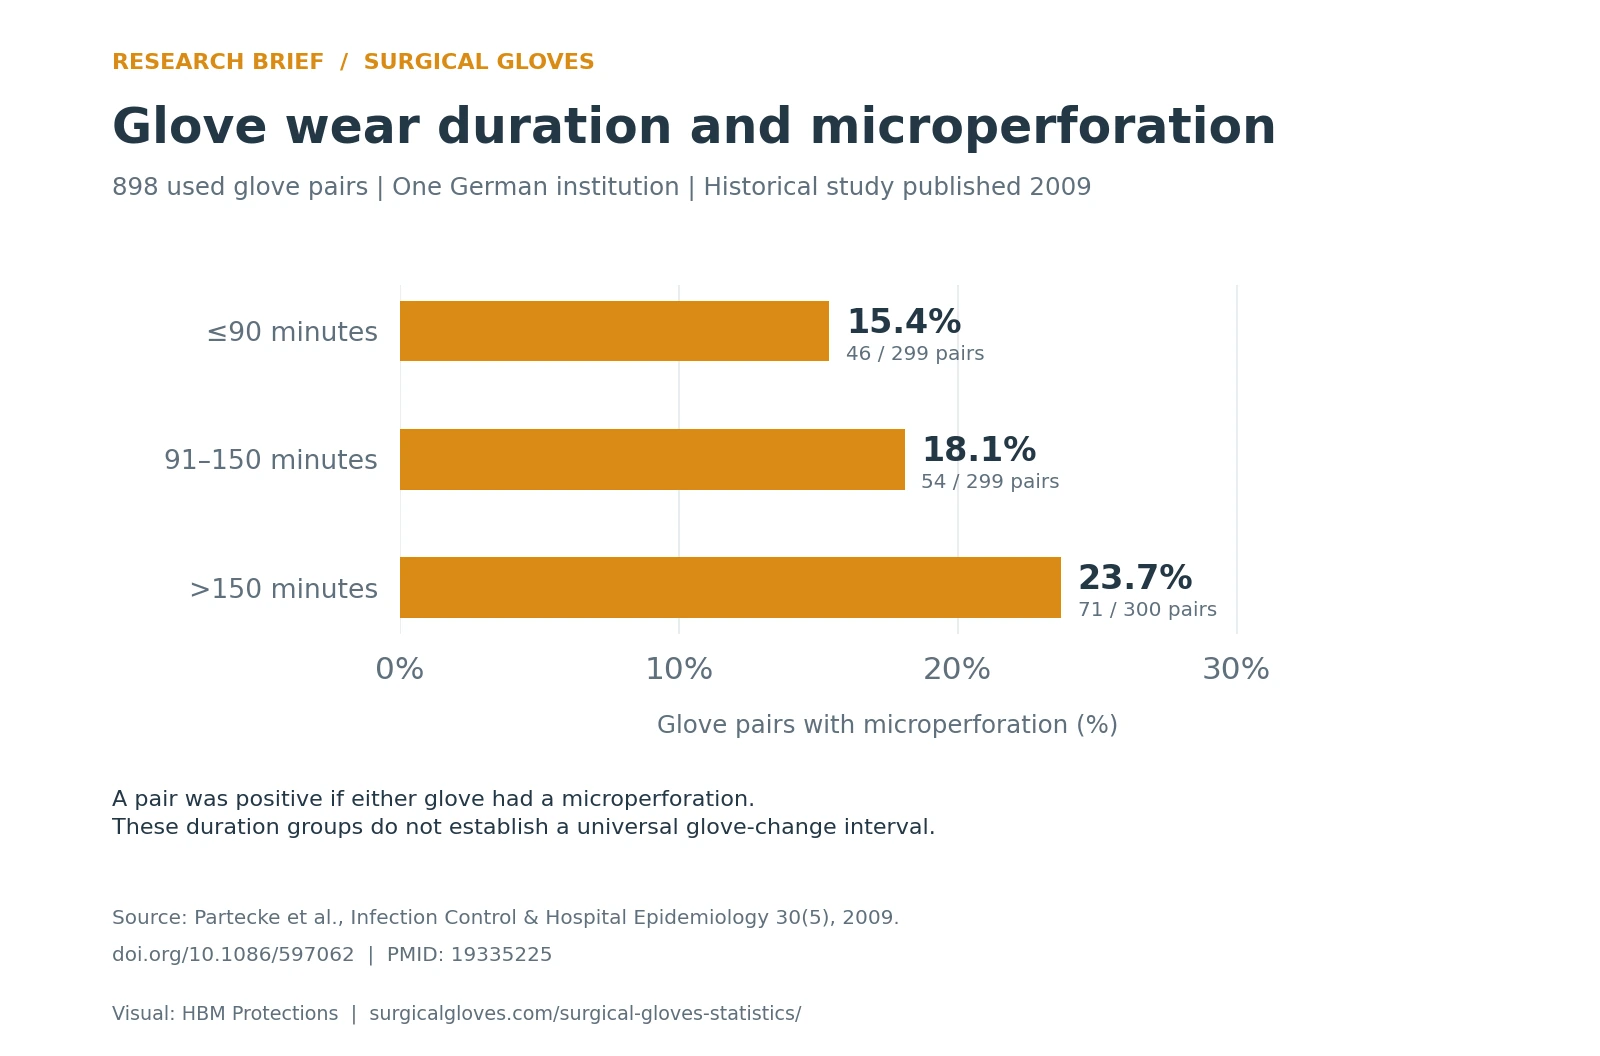
Glove-pair microperforation by wear duration; findings do not establish a universal replacement interval. Source: Partecke et al., 2009. Visual: HBM Protections.
| Metric | Value | Source |
|---|---|---|
| Microperforated pairs worn ≤90 minutes | 15.4% — 46/299 | Partecke et al., 2009 |
| Microperforated pairs worn 91–150 minutes | 18.1% — 54/299 | Partecke et al., 2009 |
| Microperforated pairs worn >150 minutes | 23.7% — 71/300 | Partecke et al., 2009 |
Calculated difference: 23.7% − 15.4% = 8.3 percentage points, using the published rounded rates. This within-study gradient does not establish a universal glove-change interval. Pair-level results cannot be directly compared with individual-glove rates.
2. Double Gloving and Barrier Protection
Most double-gloving trials measure perforation or hand contamination rather than confirmed infections. Their results should retain those endpoint definitions.
A 2025 meta-analysis reported an inner-glove perforation OR of 0.20 with double versus single gloving. Its search extended through May 2024 and included 18 randomized trials using latex gloves (Singh et al., 2025).
| Metric | Value | Source |
|---|---|---|
| Inner-glove perforation with double gloving versus single-glove perforation | OR 0.20; 95% CI 0.14–0.31 | Singh et al., 2025 |
| Matched inner-and-outer perforation with double gloving versus single-glove perforation | OR 0.10; 95% CI 0.07–0.13 | Singh et al., 2025 |
| Hand contamination, double versus single gloving | OR 0.28; 95% CI 0.14–0.54 | Singh et al., 2025 |
| Historical glove-perforation rate ratio, double versus single gloving | RR 0.29; 95% CI 0.23–0.37 | Mischke et al., Cochrane, 2014 |
The historical Cochrane review searched through June 2013. Its underlying trials overlap the wider evidence base, so the reviews should not be combined as independent observations. Odds ratios and rate ratios are also different measures.
The latex-based findings do not establish comparative performance for polyisoprene surgical gloves. Material-specific claims require evidence for the selected material and product.
3. Indicator Gloves and Perforation Recognition
Maintaining an inner barrier and making an outer breach visible are separate functions. Better detection does not by itself demonstrate fewer patient infections.
Indicator double gloves had an OR of 8.64 for intraoperative perforation detection versus single gloves in the 2025 review (95% CI 4.78–15.61). This is an odds ratio, not an 8.64-fold increase in detection probability (Singh et al., 2025).
Indicator systems should therefore be evaluated for visibility as well as barrier performance. A comparison against single gloves cannot automatically be presented as a comparison against standard double gloves.
A 2026 laboratory study found different indication areas across three polyisoprene indicator-glove brands. Eleven styles were tested, with 26 samples per style. The table reports pooled-brand medians at the same observation time (Dziak, 2026).
| Metric | Value | Source |
|---|---|---|
| Brand A median breach-indication area at 9.8 seconds | 544 mm² | Dziak, 2026 |
| Brand B median breach-indication area at 9.8 seconds | 61 mm² | Dziak, 2026 |
| Brand C median breach-indication area at 9.8 seconds | 115 mm² | Dziak, 2026 |
Brand A was Biogel; the other brands were anonymized. Mölnlycke funded the study and the author was its employee. Static testing with water under optimal lighting does not measure clinical recognition, infection prevention or Medispo performance. The finding supports product-specific evaluation rather than assuming that all indicator systems behave identically.
4. Glove Changes and Surgical-Site Infection
Glove damage is a barrier outcome; surgical-site infection is a patient outcome. Evidence linking them must distinguish observational associations from randomized interventions.
ChEETAh reported an adjusted SSI risk ratio of 0.87 for changing gloves and instruments before abdominal closure. The cluster-randomized trial recruited patients across seven low- and middle-income countries during June 2020–March 2022 (NIHR Global Research Health Unit on Global Surgery, 2022).
| Metric | Value | Source |
|---|---|---|
| SSI events under current practice | 1,280/6,768 patients | ChEETAh, 2022 |
| SSI events after combined glove-and-instrument change | 931/5,789 patients | ChEETAh, 2022 |
| Adjusted SSI risk ratio, intervention versus current practice | 0.87; 95% CI 0.79–0.95 | ChEETAh, 2022 |
Calculated interpretation: 1 − 0.87 = 13% lower adjusted relative risk, not a 13-percentage-point reduction. The trial tested a combined intervention and cannot isolate the effect of glove changes alone.
Historical observational evidence adds context: a Basel cohort using 2000–2001 data associated perforation with higher SSI odds without antimicrobial prophylaxis (adjusted OR 4.2; 95% CI 1.7–10.8), but not a statistically significant increase with prophylaxis (OR 1.3; 95% CI 0.9–1.9). These associations do not establish causation (Misteli et al., 2009).
A Turkish prospective cohort collected gloves from cesarean operations in June–October 2024. After excluding visible-perforation cases, its infection analysis compared 32 microperforation-positive operations with 505 intact-glove operations (Akbulut et al., 2025).
| Metric | Value | Source |
|---|---|---|
| Cesarean operations with visible glove perforation | 9.4% — 56/593 | Akbulut et al., 2025 |
| Superficial SSI in microperforation-positive group | 21.8% — 7/32 (percentage as reported in the source) | Akbulut et al., 2025 |
| Superficial SSI in intact-glove group | 2.2% — 11/505 | Akbulut et al., 2025 |
| Adjusted SSI odds with microperforation versus intact gloves | OR 12.705; 95% CI 4.244–38.039 | Akbulut et al., 2025 |
The adjusted association is not an intervention effect. Only 18 infections occurred, and the wide confidence interval limits precision. The source-reported percentages are preserved alongside event counts. This cohort and the Basel study differ in population, perforation definition and prophylaxis context; their odds ratios should not be treated as a time trend or pooled here.
5. AQL and Leakage Testing: What Procurement Numbers Mean
Acceptance sampling evaluates production lots. It is not a prediction of glove damage during surgery.
U.S. regulation specifies AQL 1.5 for surgeons’ gloves and 2.5 for patient examination gloves (21 CFR 800.20).
| Metric | Value | Source |
|---|---|---|
| Surgeons’ glove leakage/visual-defect acceptance quality level | AQL 1.5 | 21 CFR 800.20(c)(2) |
| Examination glove acceptance quality level | AQL 2.5 | 21 CFR 800.20(c)(2) |
| Specified leakage-test water volume | 1,000 mL | 21 CFR 800.20(b)(3) |
| Second leakage observation after filling | 2 minutes | 21 CFR 800.20(b)(3) |
These are established regulatory parameters, not new 2026 clinical observations. AQL does not mean that every accepted lot has that percentage of defective gloves.
Review product-specific test results separately from quality-system and certification documents. A certificate’s scope and the selected model’s documentation should match the intended market.

Research findings and their limits. Sources: Singh et al., 2025, ChEETAh, 2022, and 21 CFR 800.20. Visual: HBM Protections.
6. Environmental Impact Beyond the Glove Itself
Additional consumables have an environmental cost, but infection treatment also uses resources. A 2025 decision-analytic model assessed both the intervention and subsequent wound-related care.
Base-case modeling estimated 22.60 kg CO₂e lower wound-specific emissions per contaminated-dirty abdominal procedure in LMICs with glove-and-instrument change (Ledda et al., 2025).
| Metric | Value | Source |
|---|---|---|
| LMIC clean-contaminated surgery: modeled base-case reduction | 10.97 kg CO₂e/patient | Ledda et al., 2025 |
| LMIC contaminated-dirty surgery: modeled base-case reduction | 22.60 kg CO₂e/patient | Ledda et al., 2025 |
These are modeled differences, not measured savings or a carbon footprint per glove pair. The model reused ChEETAh evidence and is not independent clinical confirmation. Worst-case scenarios produced net increases, so the environmental conclusion depends on assumptions.
Surgical Gloves by the Numbers
Each row identifies a study-specific finding or regulatory parameter. These values should not be pooled into a single failure rate.
| Metric | Value | Source |
|---|---|---|
| Individual-glove perforation during intertrochanteric fracture fixation, Austria | 17.4% — 309/1,771 gloves | Santol et al., 2025 |
| Surgeons’ individual-glove perforation during intertrochanteric fracture fixation, Austria | 25.8% — 168/651 gloves | Santol et al., 2025 |
| Assistants’ individual-glove perforation during intertrochanteric fracture fixation, Austria | 12.5% — 63/502 gloves | Santol et al., 2025 |
| Scrub nurses’ individual-glove perforation during intertrochanteric fracture fixation, Austria | 12.6% — 78/618 gloves | Santol et al., 2025 |
| German single-center study: glove-pair microperforation after ≤90 minutes of wear | 15.4% — 46/299 pairs | Partecke et al., 2009; historical |
| German single-center study: glove-pair microperforation after >150 minutes of wear | 23.7% — 71/300 pairs | Partecke et al., 2009; historical |
| Inner-glove perforation with double gloving versus single-glove perforation, latex-glove trials | OR 0.20; 95% CI 0.14–0.31 | Singh et al., 2025 |
| Matched inner-and-outer perforation with double gloving versus single-glove perforation, latex-glove trials | OR 0.10; 95% CI 0.07–0.13 | Singh et al., 2025 |
| Hand contamination with double versus single gloving, latex-glove trials | OR 0.28; 95% CI 0.14–0.54 | Singh et al., 2025 |
| Intraoperative perforation detection with indicator double gloves versus single gloves | OR 8.64; 95% CI 4.78–15.61 | Singh et al., 2025 |
| SSI after combined glove-and-instrument change versus current practice in abdominal surgery, ChEETAh | Adjusted RR 0.87; 95% CI 0.79–0.95 | ChEETAh, 2022 |
| U.S. surgeons’ glove acceptance quality level | AQL 1.5 | 21 CFR 800.20 |
| U.S. examination glove acceptance quality level | AQL 2.5 | 21 CFR 800.20 |
| Modeled wound-specific emissions reduction after glove-and-instrument change, LMIC clean-contaminated abdominal surgery | 10.97 kg CO₂e/patient | Ledda et al., 2025; base case |
| Modeled wound-specific emissions reduction after glove-and-instrument change, LMIC contaminated-dirty abdominal surgery | 22.60 kg CO₂e/patient | Ledda et al., 2025; base case |
| Nepal orthopedic operations with glove perforation | 47.59% — 79/166 | Bhandari et al., 2025 |
| Nepal orthopedic individual-glove perforation | 8.81% — 117/1,328 gloves | Bhandari et al., 2025 |
| Selected German general-surgery scrub-nurse glove pairs with concealed damage | 25% — 14/57 | Euler-Schmidt et al., 2025 |
| Turkish cesarean cohort: adjusted SSI odds, microperforation versus intact gloves | OR 12.705; 95% CI 4.244–38.039 | Akbulut et al., 2025 |
| Brand A laboratory PI breach-indication area at 9.8 seconds; manufacturer-funded | 544 mm² median | Dziak, 2026 |
How This Article Was Researched
Original clinical studies, systematic reviews and regulatory text were prioritized. Figures were checked for endpoint, denominator, population and publication date. Publication year is not treated as collection year; unavailable collection dates are not inferred.
No global perforation rate was calculated. Studies counting gloves, glove pairs, operations and patients are not pooled together. Broad medical-glove market forecasts were excluded, and historical evidence is not presented as current prevalence. Research findings are not Medispo product-test results and do not establish the clinical superiority of a specific brand or material.
This is a selected evidence review, not an exhaustive systematic review or a dataset of 2026 clinical outcomes. Several findings come from the same studies, and the environmental model reuses trial evidence. The figures should therefore not be counted as independent confirmations.
Citing this resource: Attribute individual findings to the linked original studies. When referencing this article’s aggregation or interpretation, cite HBM Protections, Surgical Gloves Statistics: 30+ Data Points on Perforation, Double Gloving and Infection Prevention, reviewed October 20, 2026.
How data points are counted: The 31 study-specific data points exclude sample sizes, confidence limits, repeated summary rows and the two calculated interpretations. Four regulatory parameters are listed separately. Twelve source documents are cited. Sources are not necessarily independent: systematic reviews can overlap, and the environmental model uses ChEETAh inputs.
Update note, October 20, 2026: Added orthopedic, scrub-nurse, cesarean and laboratory indicator-system evidence; expanded the summary table. Publication dates do not make older observations current prevalence. Historical studies are retained as context, without claiming that they are the latest available evidence.

Sources
- Santol et al. — Surgical glove perforation during intramedullary nailing of intertrochanteric fractures. Scientific Reports, 2025.
- Partecke et al. — Incidence of microperforation for surgical gloves depends on duration of wear. Infection Control & Hospital Epidemiology, 2009.
- Singh et al. — Double gloving for self-protection in high-risk surgeries: a systematic review and meta-analysis. Systematic Reviews, 2025.
- Mischke et al. — Gloves, extra gloves or special types of gloves for preventing percutaneous exposure injuries in healthcare personnel. Cochrane, 2014.
- NIHR Global Research Health Unit on Global Surgery — Routine sterile glove and instrument change at the time of abdominal wound closure to prevent surgical site infection (ChEETAh). The Lancet, 2022.
- Misteli et al. — Surgical Glove Perforation and the Risk of Surgical Site Infection. Archives of Surgery, 2009.
- FDA regulation — 21 CFR 800.20, reproduced by Cornell Legal Information Institute.
- Ledda et al. — Modeled Carbon Footprint of Change of Sterile Gloves and Instruments for Abdominal Wound Closure. JAMA Network Open, 2025.
- Bhandari et al., 2025 — Prevalence of Surgical Glove Perforation in Orthopedic Surgery at Tribhuvan University Teaching Hospital: An Observational Study.
- Euler-Schmidt et al., 2025 — Higher rate of undetected intraoperative damage of latex-free surgical gloves worn by scrub nurses.
- Akbulut et al., 2025 — Surgical glove perforation in caesarean section and its association with surgical site infections: a prospective cohort study.
- Dziak, 2026 — Detecting Surgical Glove Breaches: Evaluation of Double Glove Indicator System Performance Using an In Vitro Glove Perforation Method.
For specifications and documentation for Medispo latex surgical gloves or polyisoprene options, contact us to discuss the selected products and sourcing requirements.